How-to
Why Some Patients Need Oral Surgery
Last Updated: November 7, 2026
Quick Summary
Oral surgery is needed when a dental problem is too deep, complex or structural to fix with a routine extraction or a filling. Common reasons include impacted or broken teeth below the gum line, spreading infection, jaw cysts or tumors, bite problems orthodontics cannot correct, and joint problems that do not respond to conservative care.
- Oral surgery involves deeper or complex problems, often with bone involved, while routine extraction removes a visible tooth.
- Impacted wisdom teeth are the most common reason adults need oral surgery.
- Infection that spreads into the face or neck, or keeps returning after antibiotics, can point toward surgery.
- Dentists usually review your history, exam and imaging, such as X-rays or cone-beam CT, before recommending surgery.
- Ask your dentist what findings would change the plan, and consider a second opinion if unsure.
Table of Contents
- What an Oral Surgeon Does and How Surgery Differs From a Routine Extraction
- Common Reasons for Oral Surgery in Adults
- How Dentists Decide Whether Surgery Is Necessary
- Tooth Extraction by a Dentist or Oral Surgeon: Who Should Perform It
- Alternatives to Surgery and Shared Decision-Making
- Risks, Medical Considerations and Recovery Expectations
- Booking a Consultation to Find Out If Surgery Is Right for You
- Frequently Asked Questions
What an Oral Surgeon Does and How Surgery Differs From a Routine Extraction
Most people never need oral surgery, but for some patients it is the only safe way to fix a serious dental problem. Our guide to preparing for dental surgery walks through what to expect before and after a procedure.
A routine extraction removes a tooth that is visible above the gum line, usually after numbing it with local anesthetic. Oral surgery is different.
- Routine extraction: visible tooth, local numbing, short appointment
- Oral surgery: deeper or complex problems, bone involved, sedation often offered
- Oral surgeons also treat facial injuries, jaw alignment and some oral infections
Common Reasons for Oral Surgery in Adults
Adults usually need oral surgery for a small set of reasons. Knowing them helps you ask better questions at your consultation.
Impacted and Damaged Teeth
An impacted tooth is one that cannot grow into its normal position, often because it is blocked by bone, gum or a neighboring tooth. Wisdom teeth are the most common example. Damaged teeth, such as those broken below the gum line, can also require surgical removal. Leaving an impacted tooth in place can lead to infection, cysts or damage to nearby teeth.
Jaw Misalignment, Infection and Other Conditions
Some patients need surgery to correct a bite that does not line up, a problem called malocclusion. Others have a dental abscess, a jaw cyst, or a condition that affects the temporomandibular joint, where the jaw meets the skull. Facial trauma and, less often, oral tumors also call for surgical care. Each case is different, so your dentist will explain which problem applies to you.
How Dentists Decide Whether Surgery Is Necessary
Surgery is rarely the first move.
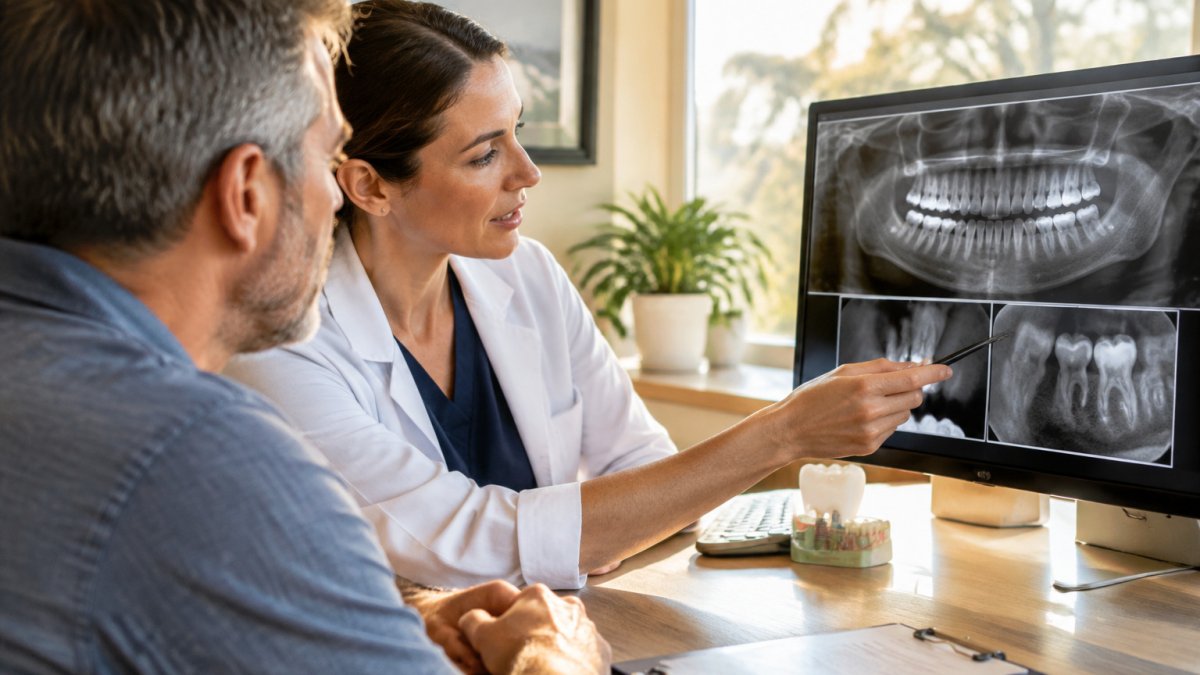
The evaluation typically moves through four steps:
- History and symptoms. Your dentist asks about pain duration, swelling, fever, bad taste, jaw locking or clicking, difficulty opening, and whether symptoms come and go. A tooth that hurts only under biting pressure points to a different problem than one that wakes you at night.
- Clinical exam. The dentist probes for mobility, gum pockets, decay below the gum line, and tenderness over the jaw joint. Limited opening, swelling that pushes into the floor of the mouth, or a tooth that cannot be touched without pain all raise the surgical index.
- Imaging. A periapical X-ray shows the tooth root and surrounding bone. A panoramic image shows wisdom teeth, the jaw joints, and the position of the inferior alveolar nerve. A cone-beam CT (CBCT) is used when a 3D view is needed to see how close a root or implant site sits to a nerve, sinus, or adjacent tooth.
- Risk comparison. The dentist weighs the risk of the procedure against the risk of waiting. A small, stable, asymptomatic problem may be monitored. A spreading infection, a fractured root below the gum, or a cyst that is enlarging changes the balance toward surgery.
A few findings reliably push the recommendation toward surgery:
- A tooth that is fractured below the gum line or has lost too much supporting bone to be restored
- An impacted wisdom tooth with decay, gum inflammation, cyst formation, or damage to the adjacent molar
- An infection that has spread beyond the tooth into the face or neck, or that keeps returning after antibiotics
- A jaw cyst or tumor that is growing or eroding bone
- A bite problem that cannot be corrected with orthodontics alone
- A joint problem that has not responded to conservative care such as a soft diet, physical therapy, or a bite guard
A few findings usually support a nonsurgical path first:
- A tooth that can be saved with a root canal and a crown
- Early gum disease that responds to deep cleaning
- A wisdom tooth that is fully erupted, healthy, and not crowding other teeth
- Mild jaw joint symptoms without structural damage
Referral to an oral surgeon is common when the case involves deep impaction, bone removal, sedation, planned implants, or a medical history that makes office-based care riskier.
Ask whether your workup included the images needed to support the recommendation.
The article lists findings that typically push the recommendation toward surgery versus those that support a nonsurgical path first.
| Finding | Usually points to | Note |
|---|---|---|
| Tooth fractured below the gum line | Surgery | Too much bone loss to restore |
| Impacted wisdom tooth with decay or cyst | Surgery | Can damage adjacent molar |
| Infection spread into face or neck | Surgery | Or keeps returning after antibiotics |
| Growing jaw cyst or tumor | Surgery | Growing or eroding bone |
| Bite not fixable with orthodontics alone | Surgery | Structural correction needed |
| Joint problem unresponsive to conservative care | Surgery | Soft diet, therapy and bite guard tried first |
| Tooth savable with root canal and crown | Nonsurgical | Restoration keeps tooth in place |
| Early gum disease | Nonsurgical | Responds to deep cleaning |
Tooth Extraction by a Dentist or Oral Surgeon: Who Should Perform It
Many straightforward extractions are done by a general dentist. A complex case is often better handled by an oral surgeon. Ask your dentist where your procedure falls.
A general dentist is usually a good fit for:
- Simple extractions of visible teeth
- Teeth that are loose from gum disease
- Baby teeth that will not come out on their own
An oral surgeon is usually the better choice for:
- Impacted teeth, especially wisdom teeth below the gum
- Teeth that have broken off near the gum line
- Cases involving bone, jaw joints or planned implants
Neither option is wrong by default. The right choice depends on how complex your case is and what your dentist recommends.
Alternatives to Surgery and Shared Decision-Making
Surgery is not always the only path. In some cases, root canal treatment, monitoring, or a restoration can keep a tooth in place. Our general dentistry services cover fillings, crowns and exams that catch problems early, often before surgery is needed.
Good care is a shared decision. Ask your dentist to explain each option, including doing nothing. Our page on preventative dental care shows how cleanings, exams and X-rays can help avoid problems that later need surgery. Ask what the likely outcome is for each choice.
Risks, Medical Considerations and Recovery Expectations
Every surgical procedure carries some risk, and the right plan depends on your health. Our article on whether general anesthesia is safe for dental implants answers common questions about sedation risk.
Medical factors that change planning include:
- Blood thinners and antiplatelet drugs. Your prescriber may adjust timing before surgery; never stop them on your own.
- Diabetes. Poorly controlled blood sugar slows healing and raises infection risk, so your dentist may coordinate with your physician.
- Bone-modifying drugs. A history of bisphosphonates or similar medications can affect jaw healing and may change whether and how surgery is done.
- Smoking. It reduces blood flow to the surgical site and is linked to slower healing and more complications; stopping before surgery helps.
- Age and anesthesia history. Older adults and patients with prior reactions to sedation need a tailored anesthesia plan.
- Pregnancy. Timing and medication choices are adjusted in coordination with your obstetric provider.
Recovery depends heavily on the procedure. The ranges below are general information, not guarantees:
- Simple extraction. Soreness and mild swelling for two to three days; most patients return to normal activity within a day or two and eat soft foods for a few days.
- Surgical extraction or impacted wisdom tooth. Swelling often peaks at 48 to 72 hours, then subsides over about a week; jaw stiffness and a soft-diet period of roughly one to two weeks are common.
- Bone grafting. The graft site needs protection while it heals; soft diet and avoidance of pressure on the area are typical for several weeks, with full integration taking months.
- Dental implant placement. Initial healing takes a few weeks, and integration with bone typically takes several months before the final restoration.
- Corrective jaw surgery. Swelling and a liquid-to-soft diet are expected for several weeks, with gradual return to normal chewing over a longer period and a structured follow-up schedule.
General aftercare that applies to most procedures:
- Use ice packs for the first 24 to 48 hours to limit swelling, then switch to gentle warmth if your surgeon advises it.
- Take pain medication as directed and do not wait for pain to become severe before the first dose.
- Keep the site clean; follow instructions on rinsing, brushing, and when to resume normal oral hygiene.
- Avoid straws, smoking, and vigorous rinsing early on, since suction and pressure can disturb the clot.
- Plan soft, cool foods for the first days and return to normal diet as comfort allows.
Call your dental office promptly if you notice any of these warning signs:
- Bleeding that does not slow after firm pressure with gauze
- Fever, or swelling that gets worse after the first few days
- Pus, a foul taste, or severe pain that medication does not control
- Numbness that lasts longer than your provider expected
- A dry socket pattern: increasing pain and a bad taste several days after extraction
- Trouble breathing or swallowing, which needs emergency care
Watch out: a clot that is dislodged by smoking, straws, or aggressive rinsing is a common cause of delayed healing, so follow the post-op sheet closely even if you feel fine.
For more on preparing for a procedure, read our guide on how to prepare for dental surgery.
Booking a Consultation to Find Out If Surgery Is Right for You
If you have been told you may need oral surgery, or if you have pain, swelling or a tooth that is causing concern, a consultation is the best next step. Bring your questions, a list of medications and any recent X-rays if you have them.
At Trinity Dental Arts, our board-certified implantologist, Dr. Xhoana Gjelaj, DMD, MAGD, DICOI, FAAID, DABOI/ID, reviews your case and explains your options in plain language.
Schedule a consultation to find out whether oral surgery is the right step for you.
Frequently Asked Questions
Why would someone need oral surgery?
Oral surgery is usually needed when a problem cannot be safely handled with routine dental care. Common examples include impacted wisdom teeth that cannot erupt properly, teeth broken below the gumline, serious gum or bone infections, jaw misalignment that affects chewing or breathing, and cysts or growths in the mouth or jaw. A dentist or oral and maxillofacial surgeon makes this call after an exam and imaging such as X-rays or a 3D scan. Whether surgery is the right step depends on your specific situation, so schedule a consultation for an individual assessment.
Is it better to have a tooth pulled by a dentist or an oral surgeon?
A general dentist can remove many straightforward teeth. An oral surgeon is generally the better choice for teeth that are impacted, broken below the gumline, fused to bone, or when sedation or a complex surgical plan is involved. Ask your dentist which provider suits your tooth, your medical history and your comfort needs. Either professional should explain the plan, anesthesia options and aftercare before the procedure.
How long does oral surgery recovery take?
Recovery depends on the procedure. Simple extractions often settle within several days, while wisdom tooth removal or jaw surgery can take one to two weeks for the most noticeable swelling and soreness to ease, with bone healing continuing for months. Following your surgeon's instructions on diet, rest, oral hygiene and medication is important. Contact your provider promptly if you develop fever, heavy bleeding, worsening pain or pus, as these can signal a complication.
Does every impacted wisdom tooth need surgery?
Not every impacted wisdom tooth needs removal immediately, but many do. Dentists typically recommend removal when a tooth causes pain, infection, cavities in neighboring teeth, gum disease, cyst formation, or crowding. Some asymptomatic teeth are monitored with regular X-rays instead. Your dentist or oral surgeon can explain the risks of removing versus keeping the tooth in your case.